SACTCHECK · YOUR TREATMENTSACTCheck home
NCCP 00525 · version 6

Ribociclib + endocrine therapy · metastatic

The usual metastatic starting dose is ribociclib 600 mg once daily on Days 1–21 followed by Days 22–28 off. Continue the prescribed AI daily or fulvestrant on its own injection schedule; add ovarian suppression when indicated. Continue while beneficial and tolerated.

Oral treatment with a planned rest week

Understand the treatment. Keep the plan manageable.

Ribociclib with an aromatase inhibitor or fulvestrant aims to control advanced HR-positive/HER2-negative breast cancer. The exact endocrine partner depends on previous treatment and menopausal status.

Open your complete treatment reference
CDK4/6 inhibitor

Ribociclib

Slows the cell-division checkpoint
CDK4/6 checkpointCheckpoint inhibitedCell cycling slows

Ribociclib blocks CDK4 and CDK6, proteins that help cells move through the cycle of division. Endocrine therapy reduces the hormone signal that can drive HR-positive breast cancer.

Keep blood and ECG appointments. Fever, jaundice, fainting, palpitations, severe rash or new breathlessness need prompt advice.

Endocrine partner

AI or fulvestrant

Reduces oestrogen-driven growth
Oestrogen pathwayAI or receptor blockadeGrowth signal reduced

An aromatase inhibitor (AI) lowers oestrogen production; fulvestrant blocks and reduces oestrogen receptors. These are alternative endocrine partners, selected by the team. Ovarian suppression is needed in pre/perimenopausal patients.

The endocrine medicine continues during the ribociclib week off. Report troublesome joint, menopausal or injection-site symptoms.

Day 1 → Day 28: a general pattern

This is a visual orientation, not a prediction of your personal cycle. It shows when some effects often emerge and which effects are not tied to a particular day.

The usual metastatic starting dose is ribociclib 600 mg once daily on Days 1–21 followed by Days 22–28 off. Continue the prescribed AI daily or fulvestrant on its own injection schedule; add ovarian suppression when indicated. Continue while beneficial and tolerated.

Day of cycle12345678910111213141516171819202122232425262728
Ribociclib tabletsOnce daily
Ribociclib planned breakNo ribociclib
Endocrine partnerAI daily OR injection schedule
Blood counts / infectionTests and symptoms guide review
Energy and bowel symptomsTiming varies; report changes early
Heart rhythm / ECGDay-14 ECG in cycle 1; symptoms any day
Optional local pre-cycle reviewLocal D25–26 window
Treatment days: Ribociclib is taken once daily on Days 1–21, followed by seven days off, in a 28-day cycle. The endocrine partner continues according to its own prescription. Treatment continues while it is helping and tolerable.
Read the phase labels: The prescription and team’s instructions determine your actual doses and any interruptions.
The bigger picture: Use the whole-treatment journey for surgery, radiation, scans and longer-term checks.
Local pre-cycle review: Day 25–26 can be a local blood / review window. It does not replace the required early checks or authorise an automatic restart.
Why these bands stay broad: Treatment bands show the source schedule. Symptom bands show possible patterns, not measured probabilities; serious effects can occur at any time. Band length does not show likelihood or severity, and the chart cannot tell you whether it is safe to receive treatment. NCCP 00525 v6 · official regimen ↗

There are no guaranteed “safe days”. Fever, shivers or suddenly feeling unwell require immediate contact. Serious symptoms override the timeline or diary.

Baseline → treatment → follow-up

Treatment and monitoring over time

Columns show sequence and general intervals, not equal periods or booked appointments. The team confirms who arranges each test, who reviews results and who authorises treatment or restart.

CheckBefore first doseCycles 1–2Cycles 3–6Later treatmentCompletion / change
Ribociclib and endocrine partnerConfirm metastatic 600 mg / AI or fulvestrant planDays 1–21 on; Days 22–28 off; fulvestrant loading visits if chosenRepeat if cleared; endocrine partner continuesWhile beneficial and toleratedReview endocrine continuation separately
Blood counts / renal / liverBaseline profilesEvery two weeks in both cyclesBefore each cycleAs clinically indicated; more often if abnormalFollow abnormalities before restart or after stopping
ECG / heart rhythmBaseline ECG; check QTcF eligibilityRepeat around cycle 1 Day 14Further ECG when clinically indicatedRepeat for symptoms, QT change or interacting medicinesNo automatic restart after a QT-related hold
ElectrolytesPotassium, calcium, magnesium and phosphorusBefore each cycle; correct abnormalitiesBefore each cycle through cycle 6As clinically indicatedReview unresolved abnormalities
Bone / endocrine healthAssess AI/OFS bone and menopausal risksSupport symptoms and adherenceAI/OFS and any injections follow their own planRepeat bone assessment according to riskLonger endocrine and bone plan continues
Cancer responseBaseline disease assessmentAssess new symptoms promptlyImaging according to consultant planContinue response and symptom reviewProgression prompts new treatment decision
The whole treatment journey

Ribociclib + endocrine therapy · metastatic: treatment and checks

HR-positive / HER2-negative metastatic breast cancer

The usual metastatic starting dose is ribociclib 600 mg once daily on Days 1–21 followed by Days 22–28 off. Continue the prescribed AI daily or fulvestrant on its own injection schedule; add ovarian suppression when indicated. Continue while beneficial and tolerated.

Read from left to right. Columns show stages, not equal lengths of time. This is a general plan: no dates or personal information are needed. Your team confirms which steps apply and arranges appointments.

On a small screen, swipe the map sideways. The checks below give the same timing in words.

Treatment, tests and reviews across the course
Care / checkBefore first doseCycles 1–2Cycles 3–6Later treatmentCompletion / change
Ribociclib and endocrine partnerNCCP 00525 · SMPCConfirm metastatic 600 mg / AI or fulvestrant planDays 1–21 on; Days 22–28 off; fulvestrant loading visits if chosenRepeat if cleared; endocrine partner continuesWhile beneficial and toleratedReview endocrine continuation separately
Blood counts / renal / liverNCCP 00525 · SMPCBaseline profilesEvery two weeks in both cyclesBefore each cycleAs clinically indicated; more often if abnormalFollow abnormalities before restart or after stopping
ECG / heart rhythmNCCP 00525 · SMPCBaseline ECG; check QTcF eligibilityRepeat around cycle 1 Day 14Further ECG when clinically indicatedRepeat for symptoms, QT change or interacting medicinesNo automatic restart after a QT-related hold
ElectrolytesNCCP 00525 · SMPCPotassium, calcium, magnesium and phosphorusBefore each cycle; correct abnormalitiesBefore each cycle through cycle 6As clinically indicatedReview unresolved abnormalities
Bone / endocrine healthNCCP 00525 · SMPCAssess AI/OFS bone and menopausal risksSupport symptoms and adherenceAI/OFS and any injections follow their own planRepeat bone assessment according to riskLonger endocrine and bone plan continues
Cancer responseNCCP 00525 · SMPCBaseline disease assessmentAssess new symptoms promptlyImaging according to consultant planContinue response and symptom reviewProgression prompts new treatment decision

What each check is for

1Before the first doseBefore first dose

Check eligibility, organ function and the exact treatment/support plan.

Ask / act: Confirm who arranges each check and who reviews it.

Sources: NCCP 00525 · SMPC

2Early toxicity checksCycles 1–2

Important toxicity can begin before the first routine review.

Ask / act: Keep early appointments and use the agreed symptom-contact plan.

Sources: NCCP 00525 · SMPC

3Benefit, tolerability and adherenceLater treatment

Longer-term treatment still needs clinical review.

Ask / act: Ask about symptom support, results and the next decision.

Sources: NCCP 00525 · SMPC

4Completion or treatment changeCompletion / change

The targeted medicine and endocrine partner may have different stop dates.

Ask / act: Confirm each medicine and the ongoing follow-up plan.

Sources: NCCP 00525

At the next review, ask

  • Which treatment phase am I in, and what happens next?
  • Which test is expected next, who arranges it, and who explains the result?
  • Who should I contact if an expected appointment has not arrived?

This map does not show whether a test has been ordered, booked or completed. Do not wait for a scheduled test if you develop new symptoms.

Sources checked 2026-10-25 · Source reconciled; independent clinical, pharmacy and patient/PPI review pending · SACTCheck v0.84.21
Printable treatment and monitoring map

The effects most relevant to this medicine

A picture of side effects

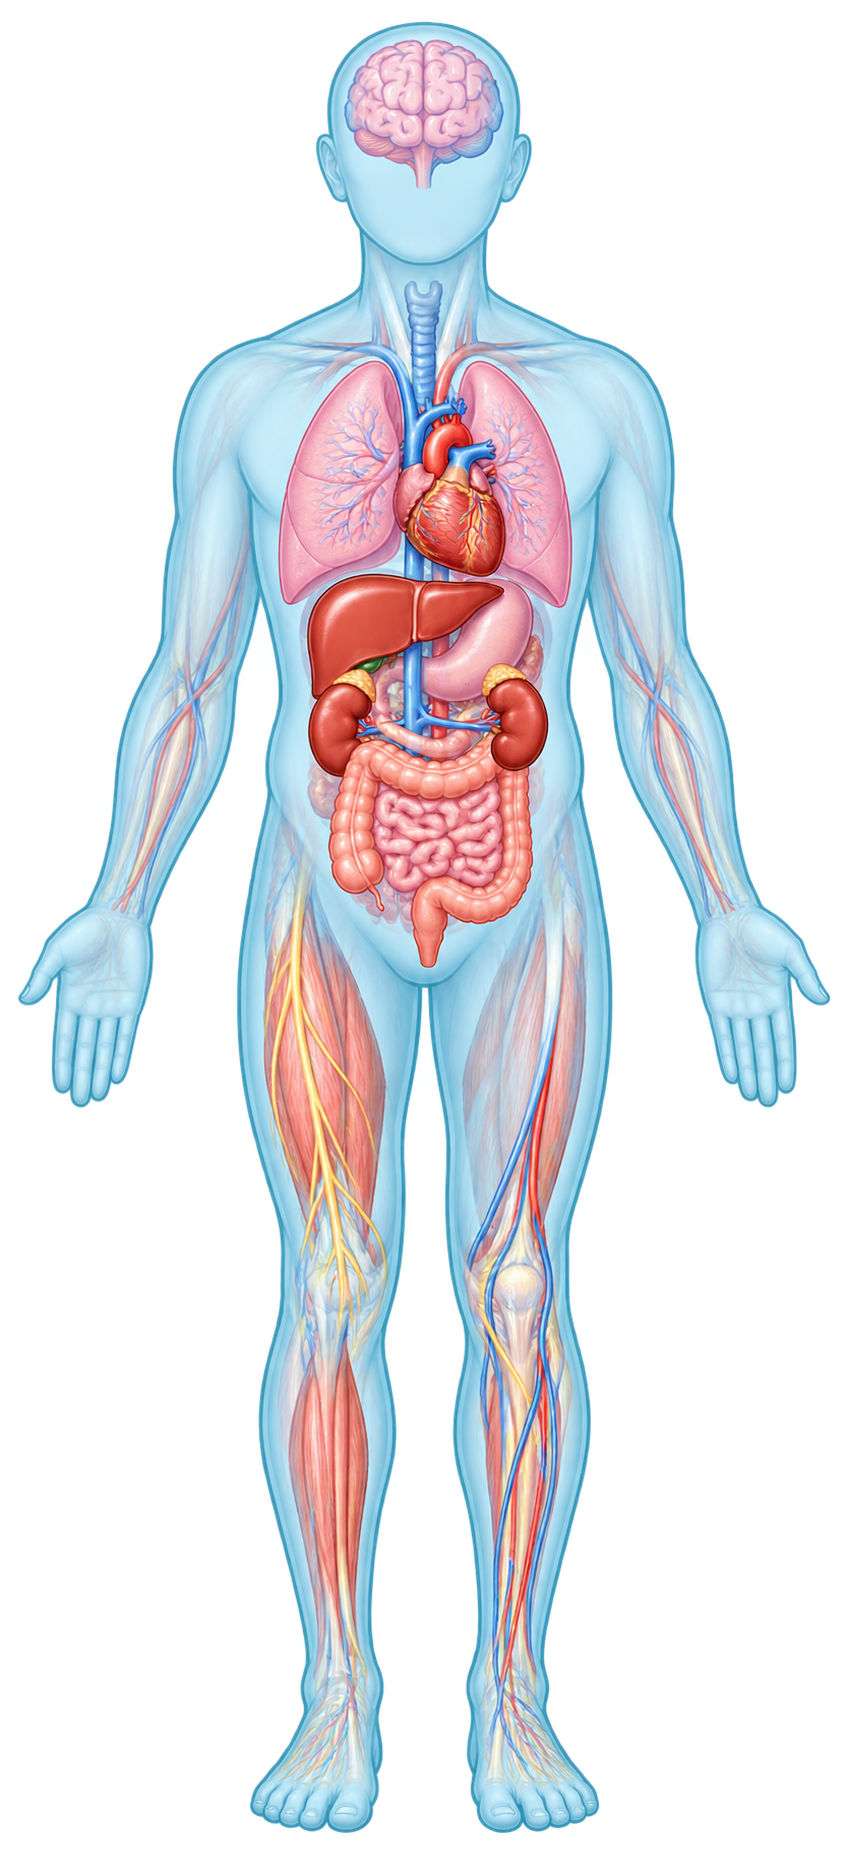
Numbered symptom boxes connect to the anatomical illustration. The medicine responsible may be uncertain; report the symptom.

1Heart rhythm / QT
Ribociclib

Baseline ECG and an ECG around Cycle 1 Day 14. Fainting or palpitations need urgent advice.

3Low neutrophils / infection
Ribociclib

Blood counts guide whether the next cycle can start. Fever, shivers or sudden illness: contact oncology immediately.

5Severe rash or blistering
Ribociclib

A widespread painful rash, blisters or peeling skin needs urgent assessment.

Full-body anatomical illustration with numbered symptom locations123456
2Liver injury
Ribociclib

Keep liver blood tests. Yellow skin / eyes, dark urine or marked upper-abdominal discomfort: call promptly.

4Lung inflammation
Ribociclib · uncommon but important

New cough or breathlessness needs prompt assessment, even between visits.

6Joints and bone health
Aromatase inhibitor / ovarian suppression

Discuss joint symptoms and keep the agreed bone-risk and DXA plan.

Selected effects, not every possible effect or a prediction. Blood-count, skin and line markers are schematic. Number and text carry meaning; colour is decorative.

This map links possible effects to the medicine that can cause them. It does not show how likely they are or diagnose a new symptom.

Support throughout treatment

Nausea support

NCCP classifies ribociclib as oral moderate–high emetic risk. The team chooses preventive or rescue antiemetics using local policy, symptoms, QT risk and drug interactions; do not reuse another regimen’s prescription.

Electrolytes and heart rhythm

Correct abnormal potassium, calcium, magnesium and phosphate as directed. Attend the baseline and cycle 1 Day-14 ECG; fainting or palpitations need urgent advice.

Counts and liver tests

Keep the early two-weekly blood tests and subsequent monitoring. Report fever, shivers, jaundice or dark urine promptly.

Endocrine treatment

The AI or fulvestrant, and ovarian suppression when prescribed, continue on their own timetable. Discuss joint, menopausal, bone and injection-site symptoms.

Daily administration

Avoid grapefruit and check interactions. Do not replace a missed or vomited dose. A clinical hold requires explicit instructions about which medicine stops and who authorises restart.

Your practical treatment guide

When to get help

Emergency: 112 / 999. Severe chest pain, major breathing difficulty, collapse or stroke symptoms need emergency help.
Contact your treating team promptly: Report new breathlessness, chest symptoms, severe diarrhoea, inability to drink, jaundice, a painful swollen leg or a severe rash promptly. You do not need to identify which medicine caused the symptom.
Your oncology team · daytimeInsert numbers here

Acute Oncology Service

Your oncology team · out of hoursInsert numbers here

Ask for medical oncology

Evenings / overnightYour agreed out-of-hours pathway

Other hospitals: use the contacts your own team provides.

Tools to take with you

One-page consent aid · Individual discussion draft · Supportive-care plan

QR code for the public treatment information
Your complete treatment reference

https://sactcheck.com/patient/00525/

Public information only. No personal information is encoded.

Sources and review

The NCCP regimen supplies the treatment rules. Separate guidelines supply the longer-term monitoring recommendations, with their qualifications retained.

Source reconciled; independent clinical, pharmacy and patient/PPI review pending