SACTCHECK · YOUR TREATMENTSACTCheck home
HER2-positive metastatic breast cancer · maintenance · NCCP 00726 v3a

Pertuzumab + trastuzumab maintenance

This maintenance treatment continues HER2 blockade to help control metastatic or unresectable recurrent HER2-positive breast cancer after chemotherapy.

PertuzumabTrastuzumab21-day cycle
Your complete treatment reference

Understand the plan. Find what you need.

Medicines, schedule, tests, side effects, daily life, with sources and practical actions.

Open complete patient reference → Explore your 21-day timeline →

Draft — independent clinical, pharmacy and patient/PPI review pending · prepared 2026-10-21

Pertuzumab and trastuzumab are given by infusion every 21 days after the chemotherapy phase of the metastatic treatment plan. Duration depends on benefit, tolerance and the agreed plan; this is not a fixed one-year adjuvant course.

How your medicines work

HER2-targeted antibody

Pertuzumab

Blocks HER2 pairing with other receptors
HER2 pairing→Pertuzumab blocks pairing→Growth signals reduced

Pertuzumab binds a different area of HER2 from trastuzumab. It limits receptor pairing, so the two antibodies act together at different points on the same growth pathway.

Report diarrhoea early, especially with poor fluid intake. Keep cardiac checks and report infusion symptoms immediately.

HER2-targeted antibody

Trastuzumab

Targets HER2 growth signals
HER2 on cell surface→Antibody binds→Growth signalling reduced

Trastuzumab binds to the HER2 protein on cells and helps reduce HER2-driven growth and recruit immune activity. HER2 testing identifies the cancers for which this approach is used.

Attend planned echoes. Report breathlessness, ankle swelling, rapid weight gain or infusion symptoms.

Baseline → treatment → follow-up

When your checks happen

Cycle numbers are examples for uninterrupted three-weekly treatment. Schedule checks by elapsed time and clinical need. Moving to maintenance does not restart the cardiac-monitoring clock. The clinical team books and reviews results; this map does not track completed tests.

CheckBefore this phaseBefore every 21-day cycleWeek 12 · around C5Weeks 24 / 36 · around C9 / C13Later / treatment change
Heart pumping test · echo / MUGAReview baseline / latest cardiac assessment and the next due dateReview symptoms; echo is not automatically needed before every infusionRepeat at 12 weeks; earlier if symptoms or impairmentContinue every 12 weeks; preserve the existing due dateNCCP 12-weekly default while treatment continues; a different interval needs an explicit specialist plan.
Blood testsBaseline FBC, renal and liver profileFBC, renal and liver tests before every cycleContinue pre-cycle blood testsContinue pre-cycle blood testsFollow abnormalities and the next treatment plan
Cancer imaging / markersRecord disease sites and the comparison scanReview new symptoms at every visitMetastatic: response scans when due under the individual planIndividual scan interval; markers only if informativeMetastatic scans commonly every 2–4 months; not an NCCP fixed-cycle rule
ECG / bone healthECG when indicated by cardiac assessment; DEXA only if endocrine / fracture risk indicatesNo automatic every-cycle ECG or DEXARisk-based clinical planRisk-based clinical planKeep any separately prescribed endocrine and bone-health follow-up
The whole treatment journey

HER2 maintenance: treatment and checks continue

Maintenance · HER2-positive metastatic / unresectable recurrent breast cancer

Pertuzumab and trastuzumab continue after the chemotherapy part of the metastatic treatment plan. Maintenance remains active treatment, with response and heart checks.

Read from left to right. Columns show stages, not equal lengths of time. This is a general plan: no dates or personal information are needed. Your team confirms which steps apply and arranges appointments.

On a small screen, swipe the map sideways. The checks below give the same timing in words.

Treatment, tests and reviews across the course
Care / checkEarlier combinationMaintenance transitionEvery 3 weeksRegular response reviewBeyond year 1
Cancer medicinesNCCP 00726Chemotherapy with HER2 treatmentReview benefit, tolerance and last dose datePertuzumab + trastuzumab infusionsContinue while benefit and tolerance support the planOngoing treatment; no fixed one-year stopping rule
Local / endocrine careMETASTATIC · EARLYPrior surgery or radiation variesDiscuss symptom-directed local treatmentRadiotherapy only if separately indicatedEndocrine therapy may be considered if HR-positiveMDT agrees any changes
Blood testsNCCP 00726Carry previous results forwardBlood count, kidney and liver testsBefore each cycleAdditional tests when indicatedContinue according to the active regimen
Heart ultrasoundNCCP 00726 · ESCCount from first HER2 exposureCheck latest echo and due intervalSymptoms reviewed every visitNCCP: echo every 12 weeks12-weekly default; interval changes require cardiac risk review
Cancer scansMETASTATICBaseline extent documentedUse prior scans as comparisonReport new symptoms between scansUsually every 2–4 months; modality / interval individualisedKeep a documented response-assessment plan
Tumour markersMARKERSConsider if informativeConfirm whether used for this personNo universal marker scheduleAdjunct to symptoms and scans, never aloneContinue only when clinically useful

What each check is for

1Heart ultrasoundNCCP: baseline and every 12 weeks during HER2 treatment

Checks heart function while treatment continues.

Ask / act: Ask when the next echo is due; a move to maintenance does not restart the clock.

Sources: NCCP 00726 · ESC

2Response imagingUsually every 2–4 months; earlier if clinically needed

A baseline scan records where the cancer is. Response is usually reviewed every 2–4 months, adjusted for the treatment, disease pace, symptoms and previous results. CT chest/abdomen/pelvis is common when appropriate; the team chooses the imaging needed for the known sites.

Ask / act: Ask what scan is planned, when results will be discussed and who to contact for new symptoms.

Sources: METASTATIC

3Tumour markers, if usefulOnly if included in the individual monitoring plan

CA 15-3 or CEA may be helpful in selected metastatic cases, especially if previously raised. They support the assessment with symptoms and imaging; a marker alone does not decide whether treatment is working or should change.

Ask / act: Ask what a change means alongside the scan and clinical review.

Sources: MARKERS

4Missed or delayed infusionWhenever a treatment gap occurs

A long gap can change the required antibody loading doses.

Ask / act: Contact the team to confirm the new prescription; do not assume the old visit plan still applies.

Sources: NCCP 00726

5Separate early-breast pathwaysAt every transition

This particular NCCP code is for metastatic/unresectable recurrent maintenance.

Ask / act: Ask the team to confirm the setting and aim on the written plan.

Sources: NCCP 00726

At the next review, ask

  • Which treatment phase am I in, and what happens next?
  • Which test is expected next, who arranges it, and who explains the result?
  • Who should I contact if an expected appointment has not arrived?

This map does not show whether a test has been ordered, booked or completed. Do not wait for a scheduled test if you develop new symptoms.

Sources checked 2026-10-21 · Source reconciled; independent clinical, pharmacy and patient/PPI review pending · SACTCheck v0.84.14

Open whole-treatment map Printable journey and checks

Day 1 → Day 21: a general pattern

This is a visual orientation, not a prediction of your personal cycle. It shows when some effects often emerge and which effects are not tied to a particular day.

Pertuzumab and trastuzumab are given by infusion every 21 days after the chemotherapy phase of the metastatic treatment plan. Duration depends on benefit, tolerance and the agreed plan; this is not a fixed one-year adjuvant course.

Day of cycle123456789101112131415161718192021
Pertuzumab + trastuzumabIV
Infusion reactionStaff observe
DiarrhoeaReport changes promptly
Cardiac symptomsAny day; keep the echo schedule
Treatment days: Pertuzumab and trastuzumab are given by infusion every 21 days after the chemotherapy phase of the metastatic treatment plan. Duration depends on benefit, tolerance and the agreed plan; this is not a fixed one-year adjuvant course.
Read the phase labels: The prescription and team’s instructions determine your actual doses and any interruptions.
The bigger picture: Use the whole-treatment journey for surgery, radiation, scans and longer-term checks.
Why these bands stay broad: Treatment bands show the source schedule. Symptom bands show possible patterns, not measured probabilities; serious effects can occur at any time. Band length does not show likelihood or severity, and the chart cannot tell you whether it is safe to receive treatment. NCCP 00726 v3a · official regimen ↗

There are no guaranteed “safe days”. Fever, shivers or suddenly feeling unwell require immediate contact. Serious symptoms override the timeline or diary.

Practical treatment guide

Your practical treatment plan

Pertuzumab and trastuzumab are given by infusion every 21 days after the chemotherapy phase of the metastatic treatment plan. Duration depends on benefit, tolerance and the agreed plan; this is not a fixed one-year adjuvant course.

STEP 1

Before the first visit

Before maintenance, review blood tests, the latest heart assessment, prior treatment response, last antibody doses and the next echo due date.

STEP 2

Plan venous access

A cannula, PICC or implanted port may be used. If a port is chosen, a trained team inserts it in a separate procedure with local anaesthetic and sometimes sedation; the team explains fasting, blood-thinner and wound instructions.

STEP 3

Infusion day

Check treatment tolerance and symptoms, then receive the prescribed pertuzumab and trastuzumab infusions with observation. Premedicines depend on previous reactions and the individual plan; they are not automatic chemotherapy premedication.

STEP 4

Home and next review

This regimen does not routinely need a take-home infusion pump. Staff disconnect the infusion; a port is de-accessed when appropriate. Keep line-care and next-visit instructions.

Port insertion and removal

The line team explains placement, dressing care and when normal activities can resume. A port is accessed with a special needle during treatment. Removal of the implanted device is a separate planned procedure when no longer needed; do not remove or adjust it yourself.

PICC care and urgent line symptoms

A PICC usually needs regular dressing and flushing appointments even between treatments. Fever, redness, swelling, pain, leakage or damage requires prompt advice. Your hospital supplies the exact care instructions.

Visit time and transport

The visit includes review, infusions and observation. Maintenance does not automatically require new loading doses; an interval of 6 weeks or longer needs review of both antibody loading schedules. Ask your team for the expected visit time.

Sources: NCCP 00726 v3a · official regimen · eviQ · PICC patient information · eviQ · implanted port patient information. Draft — independent clinical, pharmacy and patient/PPI review pending.

Regimen-specific symptoms

Recognise symptoms and act early.

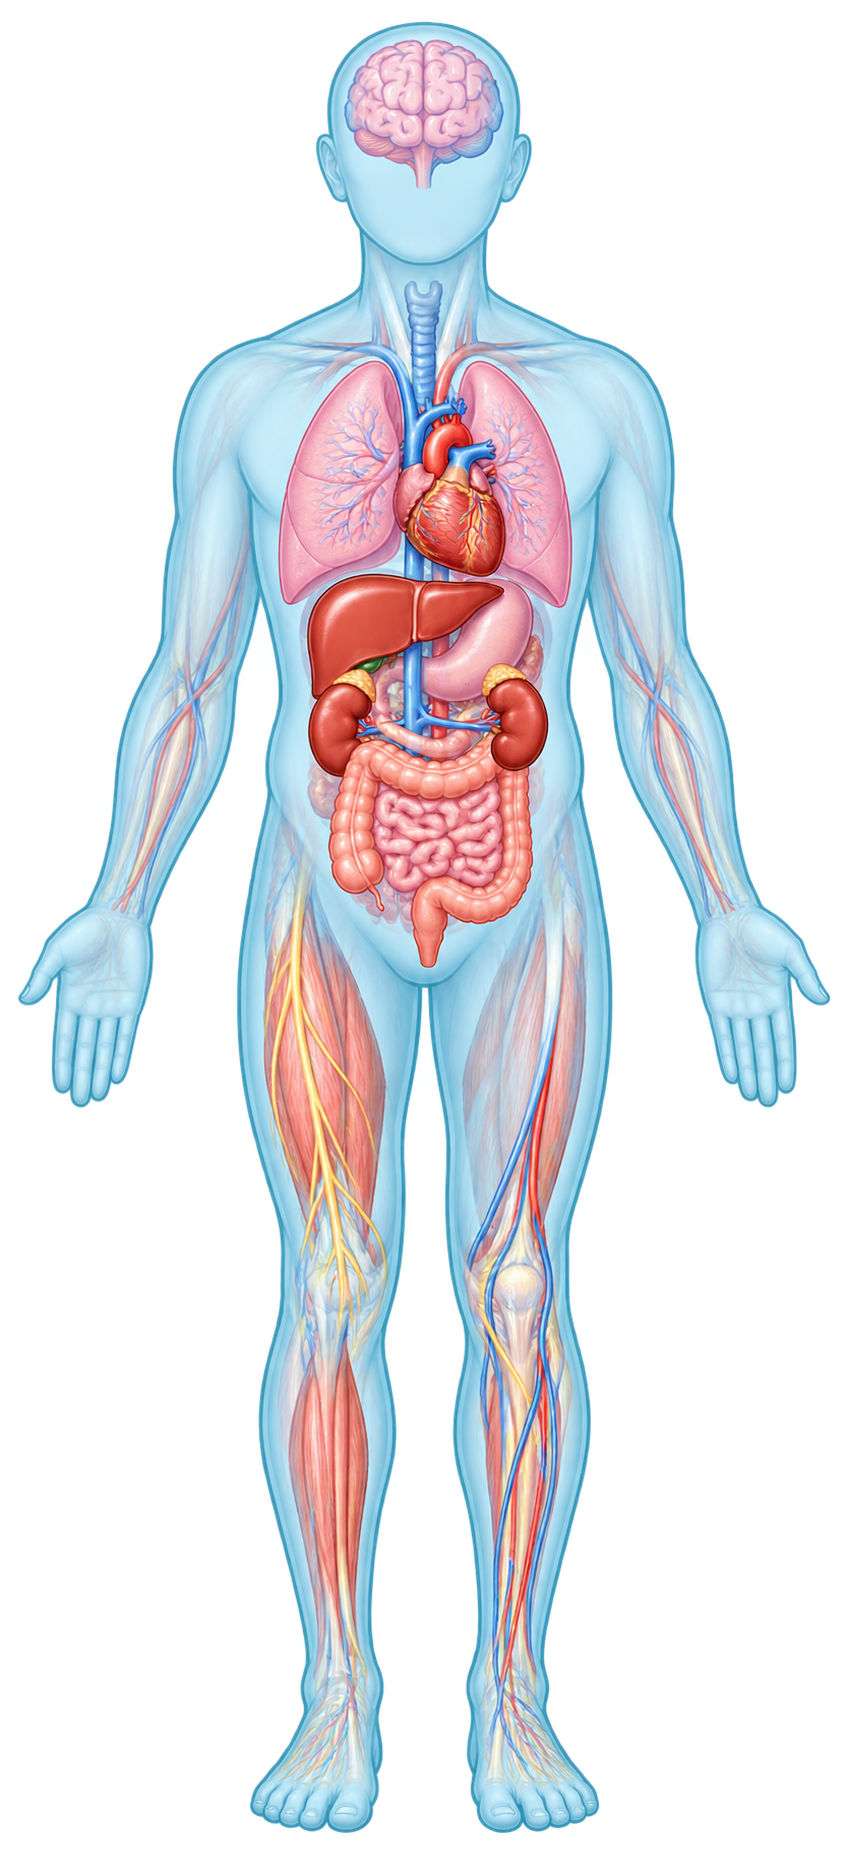
A picture of side effects

Numbered symptom boxes connect to the anatomical illustration. The medicine responsible may be uncertain; report the symptom.

1Heart pumping function
Pertuzumab + trastuzumab

Keep scheduled echoes. New breathlessness, ankle swelling or reduced exercise tolerance: contact oncology promptly.

3Infusion / allergic reaction
Both HER2 antibodies

During treatment, tell staff immediately about flushing, rash, chest tightness or breathing difficulty.

Full-body anatomical illustration with numbered symptom locations123
2Diarrhoea
Especially pertuzumab

Report frequent / watery stools early, especially with dizziness or poor fluid intake.

Selected effects, not every possible effect or a prediction. Blood-count, skin and line markers are schematic. Number and text carry meaning; colour is decorative.

Pertuzumab

  • Diarrhoea and dehydration
  • Infusion / allergic reaction
  • Heart pumping-function reduction
  • Rash and fatigue

Trastuzumab

  • Heart pumping-function reduction / heart failure
  • Infusion or allergic reaction
  • Diarrhoea and fatigue
  • Rare serious lung effects

Support around treatment

Infusion planning

Confirm the last treatment date with the team; long gaps can change the loading-dose plan.

Heart checks

Echoes continue on maintenance. Report new breathlessness, ankle swelling or rapid weight gain.

Bowel symptoms

Report diarrhoea early and follow the agreed hydration/support plan.

Response and daily life

Keep response-review appointments. Ask for support with fatigue, activity, sexual wellbeing and practical concerns.

Do not wait for the next appointment

Emergency: 112 / 999. Severe breathing difficulty, collapse, seizure or severe chest pain needs emergency help.
Contact oncology immediately for temperature ≥37.5°C or ≤36°C, shivering or suddenly feeling unwell, even with a normal temperature. Follow your own hospital’s instructions. If you cannot reach the team, seek urgent medical assessment.
Your oncology team · daytimeInsert numbers here

Acute Oncology Service

Your oncology team · out of hoursInsert numbers here

Ask for medical oncology

Evenings / overnightYour out-of-hours pathway / nearest ED

Other hospitals: use the numbers your team provides.

Report new breathlessness, chest symptoms, severe diarrhoea, inability to drink, jaundice, a painful swollen leg or a severe rash promptly. You do not need to identify which medicine caused the symptom.

Tools that travel with you

For your treatment discussion: one-page consent aid · individualised discussion draft. These support the approved local consent process.

QR code for this public regimen portal

https://sactcheck.com/patient/00726/ · QR contains no patient information.